



Broader pneumonia protection from birth

Today, countries have an opportunity to broaden protection against pneumonia, the leading infectious killer of children—and make existing vaccine budgets go further.

Pneumococcal conjugate vaccines (PCVs) already protect millions of children against Streptococcus pneumoniae, the leading bacterial cause of childhood pneumonia. New maternal RSV vaccination adds protection against a leading viral cause and a major driver of infant hospitalization. Given during pregnancy, it protects babies through their vulnerable first months.

Complementary vaccines, overlapping benefits

The benefits may work both ways: PCV vaccination has been associated with fewer RSV hospitalizations, while RSV prevention with nirsevimab has been associated with fewer hospitalizations for invasive pneumococcal disease. These findings strengthen the case for tackling bacterial and viral threats together.

However, financing broader protection is currently a challenge, as immunization budgets come under pressure. This is where optimizing PCV programs can help. Countries can release substantial savings by choosing a lower-cost PCV product, such as Pneumosil, where appropriate, and even more by switching from three to two doses of PCV, if they are eligible.
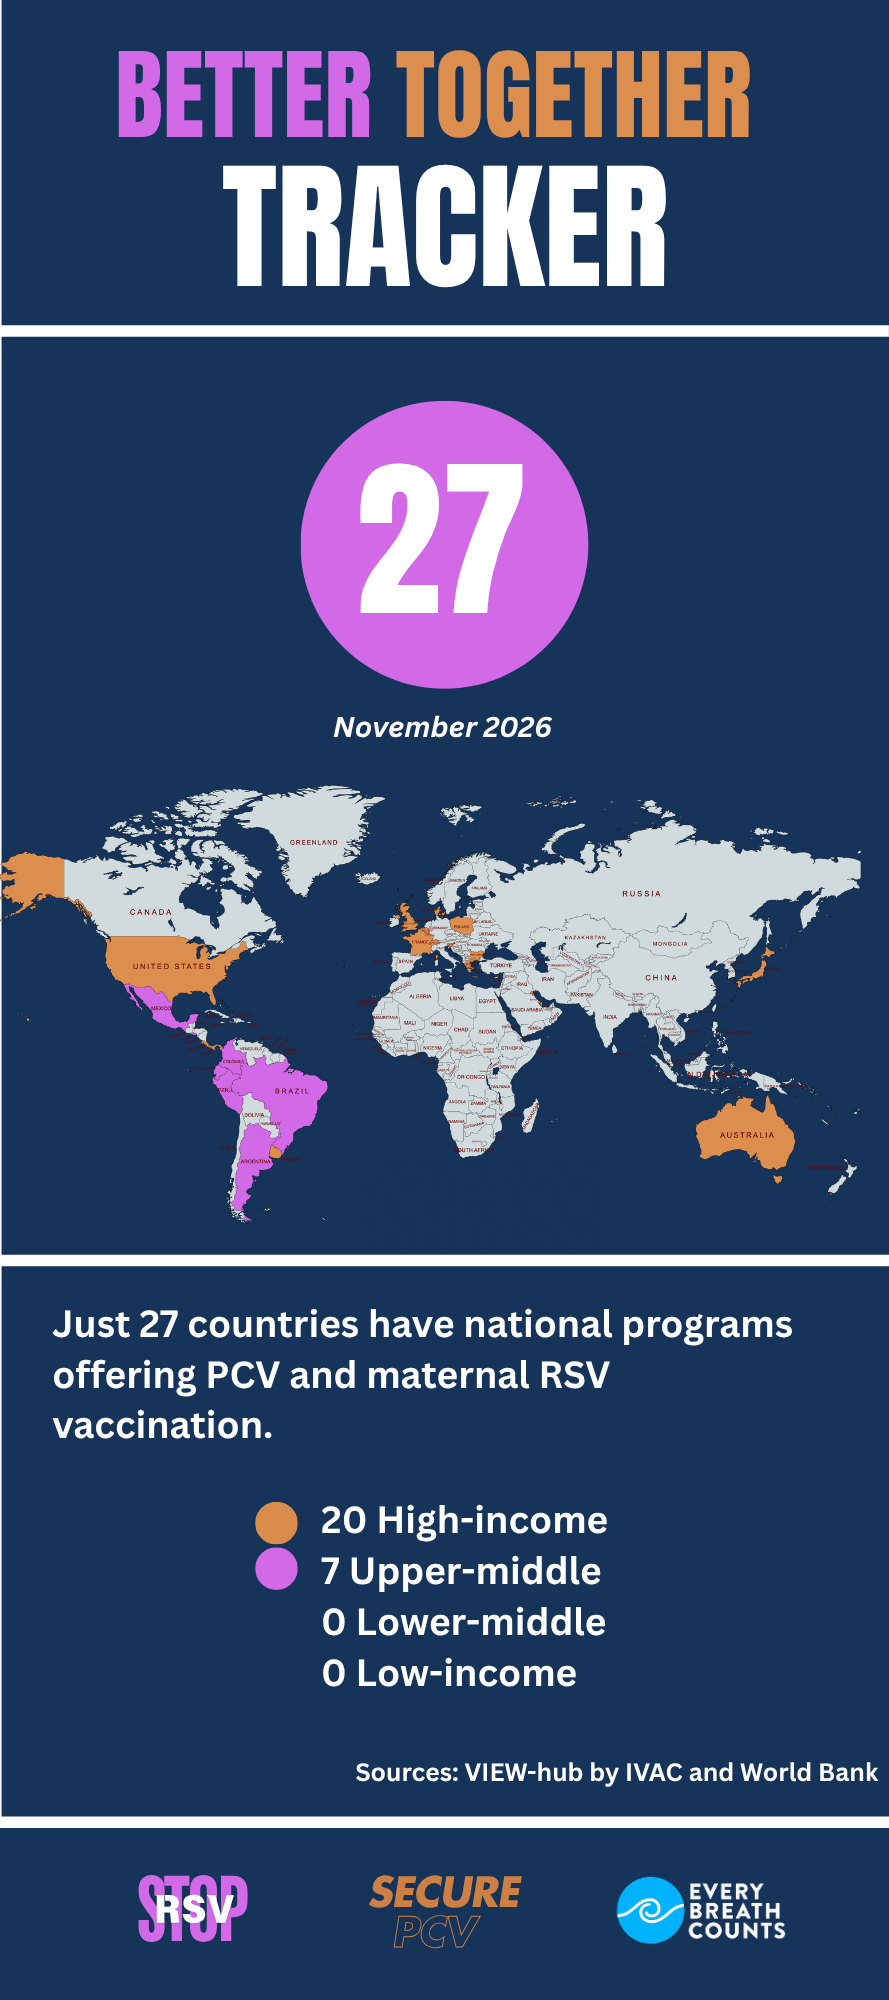

Eligible countries include those meeting WHO criteria for the PCV schedule switch—sustained high PCV and measles vaccination coverage (above 80% in previous five years).

Countries interested in pursuing both PCV product and schedule changes need to stage them over time as WHO advises against changing product and schedule simultaneously.

Explore the options for your country

Better Together connects the evidence, financing opportunities, and country experience to help governments turn PCV savings into broader protection against pneumonia.

Our country briefs use PCV-OPTIMISE to estimate savings for governments and funding partners, showing what could be available to reinvest in maternal RSV vaccination.

Explore, download, and share the Better Together brochure, country briefs, case studies, and additional resources to understand the options for your country.

Smarter PCV spending can help protect more babies, reduce hospitalizations and save more children’s lives—accelerating progress towards Sustainable Development Goal 3.2 by 2030: ending preventable newborn and child deaths.

Better Together Brochure

Three steps to Better Together


Pneumonia vaccine optimization means broadening protection and making vaccine budgets go further with three steps:

1. Switch to lower-cost PCV products and/or presentations

For Gavi-eligible and transitioning countries, Pneumosil’s five-dose vial is the lowest-cost PCV product, priced through UNICEF at US$2.00 per dose in 2026, falling to US$1.55 from 2027. For middle-income countries the price is US$4.00 per dose.

2. Switch PCV schedules

Eligible countries with mature, high-coverage programs can reduce three PCV doses to two – one infant dose plus one booster—the “1+1” schedule. This means one-third fewer PCV doses, reducing vaccine costs, injections, and storage needs.

3. Introduce RSV prevention

Savings generated from steps 1 and/or 2 can help finance the introduction of maternal RSV vaccine given during pregnancy, or nirsevimab (Beyfortus), a long-acting antibody given to babies.

Stage changes carefully. Countries planning to change both their PCV product and schedule should do so over time, as WHO advises against making both changes at once.

Better Together Country Briefs

Better Together Champions

Better Together Resources

World Pneumonia Day Presentation, November 2026

Senegal Case Study, coming soon

  • The story of the first African country to fully embrace pneumonia vaccine optimization – PCV and RSV

Better Together Evidence

A role for Streptococcus pneumoniae in viral pneumonia

Madhi SA, Klugman KP. Nature Medicine, 2004.

A South African trial where PCV reduced hospitalized pneumonia associated with respiratory viruses by 31%. The RSV-specific reduction was 22% supporting bacterial–viral interaction rather than proving RSV-specific protection.

RSV increases the virulence of Streptococcus pneumoniae

Smith CM et al. Amer Jour Resp and Crit Care Medicine, 2014.

A UK laboratory experiment showed that RSV can bind directly to pneumococcus, increasing bacterial attachment to airway cells and worsening disease. This provides a biological explanation for interaction between the pathogens.

Association between RSV and Pneumococcal Disease in Infants

Weinberger DM et al. PLOS Medicine, 2015.

A US study showing RSV activity was associated with increased pneumococcal pneumonia, and RSV hospitalizations among infants declined by 18% following PCV7 introduction. These population-level associations support a link.

PCVs Are Protective Against RSV Hospitalizations in Infants

Le H et al. Open Forum Infectious Diseases, 2023.

An Australian study of approximately 361,000 children found that receiving at least three PCV doses was associated with 21% lower RSV hospitalization in non-Aboriginal infants and 30% reduction in Aboriginal infants.

Interactions between RSV and Streptococcus pneumoniae

Besteman SB et al. The Lancet Respiratory Medicine, 2024.

A systematic review of biological, clinical, and epidemiological evidence that RSV and pneumococcus interact to worsen childhood respiratory disease and thatPCV vaccination is associated with fewer RSV hospitalizations.

Effectiveness of nirsevimab on invasive pneumococcal disease

Fafi I et al. The Lancet Infectious Diseases, 2026.

A French study of 528,000 children found that nirsevimab was associated with 36% lower adjusted odds of hospitalization for invasive pneumococcal disease over six months. This suggests benefits beyond RSV prevention.










